

Children commonly need palatal expansion in Interceptive Orthodontic Therapy. This is also called “early orthodontics” or “phase one orthodontics.”
As dentists, we often suggest orthodontic expansion (making enough room in the mouth for the tongue and the teeth) while a child is in the pre-puberty phase. This is because the upper jaw (maxilla) is believed to reach its maximum growth by age 10 or 11. The lower jaw takes a mid-puberty growth spurt. The timing of oral development treatments (like ALF appliance or palatal expanders) is based on both a child’s chronological age and dental eruption stage.
The structural development sets the stage for improved oral function and sleep. In normal growth and development, children naturally place their tongues in the roof of their mouths. When the palate is to narrow and/or the child breathes primarily through the mouth, the tongue position is low. For this second group of kids, ongoing muscle training of the tongue is crucial for the child not to revert to sleep disordered breathing. In our practice, we utilize ALF appliances rather than palatal expanders for two reasons:
1) the ALF appliance does not intrude on the tongue space, whereas many palatal expanders do. This design feature is critical for any child also going through orofacial myology therapy, oral myofunctional Therapy, swallow therapy, speech therapy, or trying to convert to nasal breathing.
2) the ALF design itself promotes proper tongue positioning, thereby allowing structure to develop around the function. We believe that when structure is developed around function, it is more integrated into the function and therefore less likely to relapse!
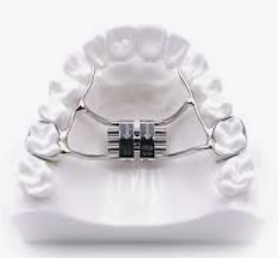
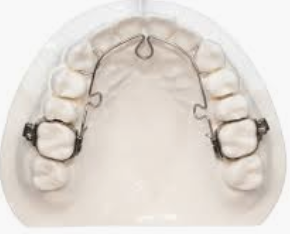
The proper position of the tongue is sometimes simply gained by being attracted to the wire loops on the ALF. Many patients tell us they find their tongues resting on the roof of the mouth even when they take out their ALFs. In some cases, the ALF can assist in positioning the tongue and the appliance is enough to change the behavior. However, if the patient has general low tone or poor overall posture, a referral to a physical therapist or orofacial myology therapist may also be necessary.
Physical therapy can help a patient retain proper tongue positioning after treatment. One way is by teaching the patient how to manage neck posture (since the base of the tongue is attached deeply to the neck). orofacial myology therapy helps by teaching specific tongue activities designed to strengthen the tongue itself along with the swallowing mechanism.
Once the shape of the palate is broad enough to hold the tongue, the tongue will hold the shape of the palate!
